















Psoriatic Arthritis: When Psoriasis Affects the Joints
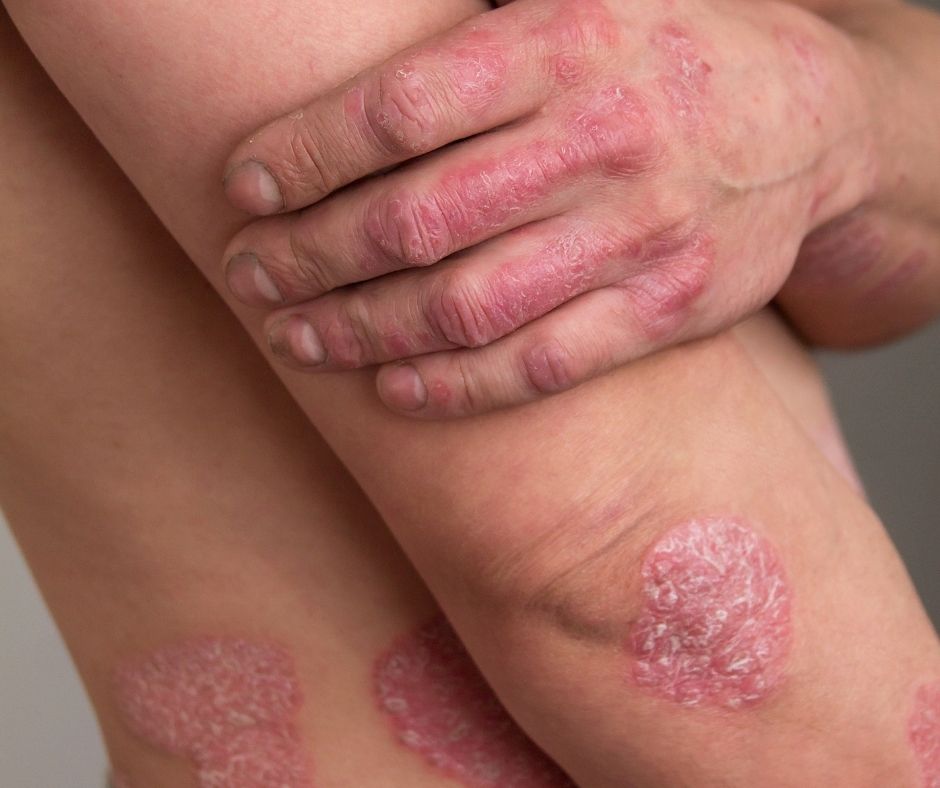
Psoriasis has many faces, and one of them is psoriatic arthritis. It is one of the chronic inflammatory joint diseases and is also known as arthritis psoriatica, psoriasis arthropatica or psoriatic arthropathy. The inflammation mainly affects the small joints of the fingers and toes, but can also involve larger joints, the points where tendons attach to bone, and the spine.
If you have psoriasis and suddenly notice joint pain, it is worth taking a closer look. The earlier psoriatic arthritis is recognised, the better your joints can be protected. In this article you will find out how to recognise it, how it progresses and what you can do yourself.
What is psoriatic arthritis?
In psoriatic arthritis, the same misdirected immune response that causes psoriasis on the skin is also directed against joints, tendons and ligaments. This leads to inflammation which, if left untreated, can damage cartilage and bone.
How many people with psoriasis develop psoriatic arthritis depends very much on how you count. Figures of up to 20 to 30 % are often quoted, and the Deutscher Psoriasis Bund speaks of around one third. A large population-based study from the USA, by contrast, found 5.1 % within 20 years. What is certain: the risk is clearly increased with psoriasis.
The condition most commonly appears between the ages of 35 and 55, but it is possible at any age. Children with psoriasis can also be affected, although at around 1 % this is rare. In children, the joint symptoms often appear before the psoriasis on the skin, which makes the correct diagnosis difficult. For most adults it is the other way round: the skin is affected first, and the joints often follow only years later.
Who is at higher risk?
Although many studies have been carried out on the risk factors for psoriatic arthritis, comparatively little is known about which features of psoriasis are linked to its occurrence. There are, however, some indications:
- Severe psoriasis: According to studies, the risk is increased further with pronounced psoriasis. One hypothesis put forward by researchers: larger plaques offer microorganisms more surface area to settle on and could serve as a kind of entry point. The ongoing immune response to this could contribute to chronic inflammation, including in the joints. This mechanism has not yet been proven.
- Psoriasis on the scalp: In the US study mentioned above, people with scalp psoriasis had an almost 4-fold higher risk of developing psoriatic arthritis than people with psoriasis without scalp involvement. You can read more about this in our article on psoriasis on the scalp.
- Nail changes (nail dystrophy): Changes in the structure or colour of the fingernails or toenails are very common in psoriatic arthritis, affecting up to 80 % of those with the condition. People with psoriasis and nail dystrophy have around a 3-fold higher risk of later developing psoriatic arthritis than those without nail changes.
- Psoriasis in the buttock and anal area: In the study, involvement of this area was also associated with roughly double the risk.
- Genetic predisposition: Heredity plays a major role. In a Canadian study, around 8 % of the parents, siblings and children of people with psoriatic arthritis also had psoriatic arthritis, and around 15 % had psoriasis. That is many times more common than in the general population.
Psoriatic arthritis: symptoms and signs

The course of psoriatic arthritis is highly individual, so the symptoms vary accordingly. These symptoms are typical:
- Joint pain, redness and swelling of individual joints, often asymmetrical, i.e. only on one side of the body
- Morning stiffness: the joints feel stiff after getting up or after sitting for a long time, and it gets better with movement
- Nail changes such as pitting, discolouration, thickening or a nail that lifts off
- Pain where tendons attach to bone (enthesitis), for example at the heel, the Achilles tendon or the sole of the foot
- Back pain, especially in the lower back, which gets worse at rest and at night
- Fatigue and a general feeling of being unwell, sometimes also muscle pain
- Deformed joints and destruction of joint cartilage and bone, especially after a long, untreated course
Fingers and toes: sausage fingers and sausage toes
Individual joints of the fingers and toes can be affected, as can all the joints of one finger or toe. If an entire finger or toe is evenly swollen, this is called dactylitis, popularly known as “sausage finger” or “sausage toe”. It is considered a typical sign of psoriatic arthritis. The end joints of the fingers, i.e. the joints directly below the nail, are also frequently affected.
The swelling occurs at irregular intervals and may subside over time, but it does not have to. Psoriatic arthritis can also cause bone to form around the affected joints, which restricts their mobility.
Psoriatic arthritis in the back: inflammation or tension?
In some people, the spine or the sacroiliac joints in the lower back also become inflamed. Because back pain is so common, this is easily overlooked. Experts from the international spondyloarthritis society ASAS have described features that point more towards inflammatory back pain:
- The pain starts gradually, not suddenly after strain.
- It begins before the age of 40.
- It is worse at night and can wake you up.
- Movement improves it, rest does not.
If several of these points apply and the pain lasts longer than three months, mention it at your GP or dermatology practice. These features do not replace a diagnosis.
Nail psoriasis as a warning sign
Because nail changes are so common in psoriatic arthritis and often precede the joint symptoms, it is worth taking a close look at your fingernails and toenails. Pitting, yellowish-brown “oil spots” or brittle, thickened nails are a good reason to have your joints checked at your next examination as well. How to recognise the typical signs and tell them apart from nail fungus is explained in our guide to psoriasis of the nails.
Osteoarthritis or psoriatic arthritis?
Joint pain is not automatically psoriatic arthritis. Especially from middle age onwards, osteoarthritis, i.e. wear and tear of the joints, is very common, and the two can also occur at the same time. The most important difference: osteoarthritis is wear and tear, psoriatic arthritis is inflammation. You can often tell from the pattern of pain.
| Feature | Psoriatic arthritis | Osteoarthritis |
|---|---|---|
| Cause | Inflammation caused by the immune system | Wear and tear of the joint cartilage |
| Pain | At rest and at night, improves with movement | On exertion, improves with rest |
| Morning stiffness | Often longer than 30 minutes | Usually only brief (“start-up pain”) |
| Swelling | Soft, warm, often an entire finger or toe | Rather bony thickening |
| Typical sites | Finger and toe joints, tendon attachments, back | Knee, hip, finger joints, base of the thumb |
| Accompanying signs | Psoriasis, nail changes, fatigue | No skin involvement |
The table helps you to classify your symptoms, but it does not replace an examination. If you are unsure, have it checked by a doctor.
Course: how does psoriatic arthritis develop?
Psoriatic arthritis usually progresses in flare-ups: phases with severe symptoms alternate with calmer periods in which the inflammation almost or completely disappears. Some people have only a few joints affected for years, while in others the inflammation spreads to more joints or the spine. Only a small proportion develop a particularly severe, deforming form.
What can trigger a flare-up?
Frequently cited triggers are stress, infections, injuries or overloading of a joint, and a flare-up of psoriasis on the skin. Many people also find the cold hard to cope with; you can read more about this in our article on psoriasis in winter.
How long does a flare-up last and what helps?
How long a flare-up lasts varies greatly, from a few days to several weeks. It often announces itself: morning stiffness lasts longer, a joint becomes warm and tender or you feel unusually exhausted. During a flare-up, many people find these steps helpful:
- Rest it, but don’t immobilise it: take the strain off the affected joint, but keep moving it gently so it doesn’t stiffen.
- Cool it: many people find a hot, swollen joint feels better with cool compresses. Always place a cloth between your skin and the cold pack.
- Write it down: note which joints are affected and what happened beforehand. Over time, this helps you recognise your personal triggers.
- Get in touch: if a flare-up doesn’t settle, new joints are affected or your current treatment isn’t enough, speak to your rheumatology practice promptly.
What happens without treatment?
Without treatment, the persistent inflammation can destroy cartilage and bone. Damage to the joints cannot be reversed later on. That is why an early diagnosis is so important: if the inflammation is slowed down in time, joint damage can often be avoided. Psoriatic arthritis is also more often accompanied by cardiovascular disease and psychological strain. You can find out how skin, joints and mind are connected in our article on psoriasis and the mind.
Diagnosis: how is psoriatic arthritis detected?

An early diagnosis is important in order to treat psoriatic arthritis appropriately. Diagnosis and therapy should be carried out by a rheumatologist, ideally in consultation with your dermatology practice. Together, an individually tailored treatment plan for skin and joints can be drawn up.
There is currently no single test that reliably detects psoriatic arthritis. The diagnosis is made up of several components:
- Consultation and examination: Which joints are affected, since when, and what is the morning stiffness like? Do you or your family have psoriasis? Your skin and nails are also examined.
- Blood values: Inflammation markers may be raised, but are not always. Rheumatoid factor is typically negative in psoriatic arthritis. This helps to distinguish it from rheumatoid arthritis. Important: normal blood values do not rule out psoriatic arthritis.
- Imaging: Ultrasound and MRI show inflammation early on, while X-rays are often still unremarkable at the beginning.
To classify the condition, doctors can draw on the CASPAR criteria, among others. They support the classification but do not replace the overall clinical assessment. Among other things, the criteria take into account existing psoriasis or psoriasis in the family, nail changes, sausage fingers, a negative rheumatoid factor and typical changes on X-ray.
What helps with psoriatic arthritis? Treatment at a glance
Psoriatic arthritis cannot yet be cured, but today it can be treated well. The aim is to stop the inflammation, relieve pain and preserve the joints in the long term. In the best case, the condition settles down (remission). You decide which treatment is right together with your rheumatology practice. Broadly, there are these components:
- Anti-inflammatory painkillers (NSAIDs) relieve pain and swelling, but do not slow the disease in the long term.
- Cortisone injections directly into the joint can calm individual, severely inflamed joints.
- Disease-modifying drugs such as methotrexate act on the immune system and can slow progression.
- Biologics and newer targeted drugs intervene specifically in the inflammatory process and often work on skin and joints at the same time.
- Physiotherapy, occupational therapy and functional training maintain mobility and strengthen the muscles.
Because skin and joints are affected by the same inflammation, it is worth keeping an eye on both together.
Everyday life with psoriatic arthritis: what you can do yourself

Alongside medical treatment, there is quite a lot you can do in everyday life to help your joints feel better:
- Keep moving: Joint-friendly sports such as swimming, aqua fitness, cycling, Nordic walking or yoga keep the joints mobile and strengthen the muscles. During an acute flare-up, take it down a gear; you usually don’t have to keep completely still.
- Watch your weight: Excess weight puts strain on the joints and can promote inflammation. Even moderate weight loss can relieve symptoms.
- Avoid smoking: Smoking worsens the course of psoriasis and can reduce the effect of some medicines.
- Eat a balanced diet: There is no miracle diet for psoriatic arthritis. However, a balanced diet with plenty of vegetables, wholegrains, pulses, nuts and fish and little processed meat, sugar and alcohol can help. You can read how the gut and psoriasis are connected in our article on the power of the gut in psoriasis.
- Reduce stress: Relaxation techniques, enough sleep and fixed rest periods can help to prevent flare-ups.
- Heat or cold: Many people find warmth pleasant for stiff joints, but cooling better during an acute, hot flare-up. Try out what feels good for you.
- Look after your skin: Well-cared-for skin makes everyday life with psoriasis easier. You can find gentle options in our article on natural remedies for psoriasis.
Skincare does not act on the joints, but it can support the skin and nails in psoriasis. The Pso Kit with Skin Balm, Cream forte and Scalp Oil has been developed specifically for care in psoriasis. For cracked, brittle nails and irritated cuticles, there is our Nail Balm. Neither replaces medical treatment.
Suspected psoriatic arthritis: your checklist for the doctor’s appointment
If you have psoriasis and your joints hurt, swell or are stiff in the morning for more than a few days, mention it to your GP or dermatology practice. They can refer you to a rheumatology practice. With a little preparation, you will get more out of the appointment:
- Note down which joints are affected, since when, and whether the symptoms come and go.
- Write down how long the morning stiffness lasts and whether movement helps.
- Take photos of swollen fingers, toes or nail changes, because they may have just subsided on the day of the appointment itself.
- Keep a short flare-up diary for a few weeks with symptoms, possible triggers and the condition of your skin.
- Mention whether psoriasis or psoriatic arthritis runs in your family.
- Bring a list of your medicines and previous treatments.
Don’t wait too long: if psoriatic arthritis is recognised early, it can usually be treated so that your joints stay mobile.
Frequently asked questions about psoriatic arthritis
Can psoriatic arthritis be cured?
No, psoriatic arthritis is a chronic condition and cannot yet be cured. With suitable treatment, however, the inflammation can often be controlled so well that many people live with few or no symptoms for a long time.
Can you have psoriatic arthritis without psoriasis on the skin?
Yes, that is possible. In some people, the joint symptoms begin before the psoriasis shows, and in children this is even common. Sometimes the skin is only affected in hidden places, such as the scalp, the cleft between the buttocks or the nails.
Is psoriatic arthritis hereditary?
There is a clear hereditary predisposition: in one study, around 8 % of the parents, siblings and children of people with psoriatic arthritis also had psoriatic arthritis, and around 15 % had psoriasis. However, only the tendency is inherited, not the disease itself. Whether it breaks out also depends on other factors.
Is psoriatic arthritis contagious?
No. Psoriatic arthritis is a disease of the immune system and cannot be passed from person to person, any more than psoriasis can.
Which doctor is responsible for psoriatic arthritis?
Diagnosis and treatment are carried out by a rheumatologist, ideally in collaboration with your dermatology practice. Your GP practice can also be a first point of contact and refer you on.
Does psoriasis automatically cause joint pain?
No. Most people with psoriasis do not develop psoriatic arthritis. However, the risk is increased, so you should take new joint pain, swelling or morning stiffness seriously and have it checked.
Is heat or cold better for psoriatic arthritis?
It depends on the phase. When joints are stiff without acute inflammation, many people find warmth pleasant, such as a warm bath. If a joint is hot and swollen during a flare-up, cooling usually feels better. Try out what works for you.
What degree of disability (GdB) applies to psoriatic arthritis?
There is no fixed value for the diagnosis. In Germany, the degree of disability (GdB) depends on how much your skin and joints restrict you in everyday life. It is based on the German medical assessment guidelines (Versorgungsmedizinische Grundsätze). You apply to the pension office (Versorgungsamt) in your federal state, and medical reports help with the assessment.
Which sports are good for psoriatic arthritis?
Joint-friendly sports such as swimming, aqua fitness, cycling, Nordic walking or yoga. They keep the joints mobile and strengthen the muscles. During an acute flare-up, you should adapt your training.
Sources
- Wilson FC et al.: Incidence and Clinical Predictors of Psoriatic Arthritis in Patients With Psoriasis: A Population-Based Study. Arthritis & Rheumatism, 2009 (National Library of Medicine)
- Sobolewski P et al.: Nail involvement in psoriatic arthritis. Reumatologia, 2017 (National Library of Medicine)
- Psoriatic arthritis: from pathogenesis to therapy. Arthritis Research & Therapy, 2009 (Biomedcentral)
- Deutscher Psoriasis Bund: Psoriatic arthritis
- Chandran V et al.: Familial aggregation of psoriatic arthritis. Annals of the Rheumatic Diseases, 2009 (National Library of Medicine)
- Sieper J et al.: New criteria for inflammatory back pain in patients with chronic back pain (ASAS). Annals of the Rheumatic Diseases, 2009 (National Library of Medicine)
- Farbenhaut: Age and onset of psoriasis